

Migraine surgery was originally developed by Dr. Bahman Guyuron in Cleveland, Ohio, after couple of his cosmetic patients reported significant improvement or complete elimination of their migraine headaches following a forehead lift procedure. Following this discovery, numerous clinical studies were performed across multiple medical centers to validate the safety and efficacy of the procedure.
Dr. Ali Totonchi has been deeply involved in extensive research regarding migraine surgery from the beginning, has frequently presented at major medical conferences, and has proudly served as the President of the Migraine Surgery Society.
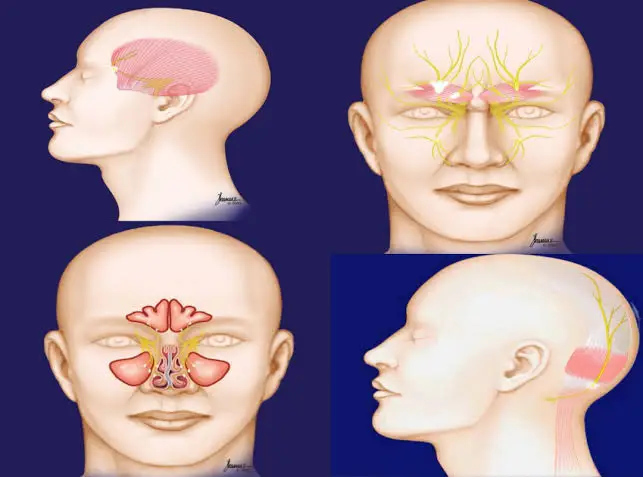
During migraine surgery, peripheral nerves in the head and neck area that are compressed, irritated, or responsible for triggering migraine pain are targeted. These nerve compression points are surgically deactivated or decompressed during the procedure. The vast majority of these surgeries are minimally invasive, short, and performed safely in an outpatient setting.
Migraine headaches are frequently linked to specific anatomical regions, categorized into distinct trigger sites:












Migraine surgery is a specialized option for individuals suffering from chronic, debilitating headaches that do not respond sufficiently to standard medical treatments.
Before being considered for surgery, all patients must undergo a thorough evaluation by a licensed headache specialist or neurologist. This step ensures a proper clinical diagnosis and rules out alternative underlying headache disorders that cannot be treated via peripheral nerve decompression.
To ensure the highest likelihood of a successful outcome, Dr. Totonchi requires patients to complete a four-week headache diary prior to their initial consultation. This day-by-day log should detail:
Patients will also be asked to complete several clinical questionnaires before their appointment. During your consultation, Dr. Totonchi will comprehensively review your medical history, analyze any relevant clinical imaging, and perform a thorough physical examination to determine if you are a strong candidate for surgery. In some cases, he may perform a diagnostic nerve block or other screening treatments during the visit to confirm your trigger sites and ensure you have a strong likelihood of benefiting from the procedure.
Most migraine surgeries are performed on an outpatient basis, allowing patients to go home the same day. On average, decompressing each individual trigger site takes approximately 1-2 hours to perform.
Published clinical studies demonstrate that 80% to 90% of patients respond favorably to migraine surgery, experiencing at least a 50% reduction in the frequency, intensity, and overall severity of their headaches. Approximately 10% to 20% of patients do not experience a significant change in their symptoms.
A meticulous, initial clinical evaluation is the single most critical factor in identifying the ideal candidates for this procedure. Because of this, active patient cooperation in accurately filling out the pre-consultation logs and questionnaires is incredibly vital.
It is important to understand that migraine surgery differs significantly from procedures like a cholecystectomy (gallbladder removal), where a single organ is removed and symptoms immediately vanish. Migraine management is a sequential process. After successfully treating a primary trigger point, a secondary trigger point may occasionally become active. As a result, some patients may require a staged approach or need to undergo surgery in a different area or at the same trigger site to achieve full relief.
While clinical research confirms that these peripheral procedures are highly safe, every surgical option carries some inherent risks. Potential complications, though rare, may include:
It is reassuring for patients to know that migraine surgery is not brain surgery. The procedure is performed entirely outside the skull, focusing strictly on the small, peripheral nerves located within the superficial tissues of the head and neck.or inside the nose.